Emergency Dentist Care for Emergency Root Canal Needs
A severe toothache has a way of taking over everything. It can wake someone at 2 a.m., make cold air feel sharp, turn a sip of coffee into a jolt, and leave even a calm person pacing the kitchen floor. When the pain comes from the center of the tooth, not just the gumline or a cracked filling, the problem may have reached the pulp, where nerves and blood vessels live. At that point, routine dental care can quickly become urgent care.
This is where an Emergency Dentist plays a critical role. Not every bad toothache needs a root canal that same day, but some absolutely do need prompt evaluation, pain control, and a plan to stop infection from spreading. In practice, emergency dental care for root canal needs is rarely just about one procedure. It is about diagnosis under pressure, reducing pain fast, preserving the tooth when possible, and knowing when a case needs same-day treatment versus stabilization and close follow-up.
The distinction matters. Patients often hear the phrase “you need a root canal” and imagine a single event. Real emergency care is more nuanced. A tooth can be inflamed beyond recovery, infected, cracked below the gumline, or so structurally compromised that extraction may be the better option. A skilled emergency dentist does not just treat pain. They sort through these variables quickly and make the safest decision with the best long-term odds.
When a toothache becomes a root canal emergency
Many dental aches are unpleasant but manageable for a day or two. A root canal emergency feels different. The pain often has a deep, throbbing quality. It may linger long after hot or cold contact, or it may become constant and spontaneous, with no trigger at all. Some patients describe it as a heartbeat inside the tooth. Others say the pain radiates into the jaw, ear, temple, or neck and becomes hard to pinpoint.
Swelling is another red flag. A puffy gum around one tooth, a tender bump that looks like a pimple, facial fullness, or swelling under the jaw can all point to an advancing infection. Sometimes the pain is intense. Sometimes it strangely eases off, only to be replaced by pressure, a bad taste, or drainage. That can happen when the pulp dies and pressure shifts. People often misread that as improvement. Clinically, it can signal a serious infection that still needs treatment.
There are also mechanical clues. A tooth that hurts sharply when biting, feels high against the opposing tooth, or suddenly becomes very sensitive after a deep filling may have inflamed pulp tissue. Cracks complicate the picture. A vertical crack can mimic root canal pain but also reduce the chance that the tooth can be saved. Trauma adds another layer. A blow to the mouth can damage the nerve even when the tooth looks intact from the outside.
From experience, some of the most urgent cases are not the loudest ones. A patient with mild pain but obvious facial swelling may need faster intervention than a patient with dramatic pain from reversible inflammation. Pain matters, but infection pattern, swelling, fever, difficulty swallowing, and overall health matter just as much.
What an Emergency Dentist is actually looking for
When someone arrives in distress, the first priority is not to rush into drilling. It is to identify the source of pain accurately. Teeth can refer pain in deceptive ways. A lower molar can feel like Smyle Dental Bakersfield Emergency Dentist an earache. Sinus pressure can mimic upper tooth pain. Clenching can make multiple teeth sore at once. The emergency dentist has to narrow the problem down quickly but carefully.
That process usually starts with a focused history. When did the pain begin? Is it triggered by temperature or biting? Does it wake you at night? Has there been swelling, drainage, fever, or recent dental work? These details are not small talk. They help distinguish reversible inflammation from irreversible pulpitis, necrotic pulp, abscess, fracture, or periodontal involvement.
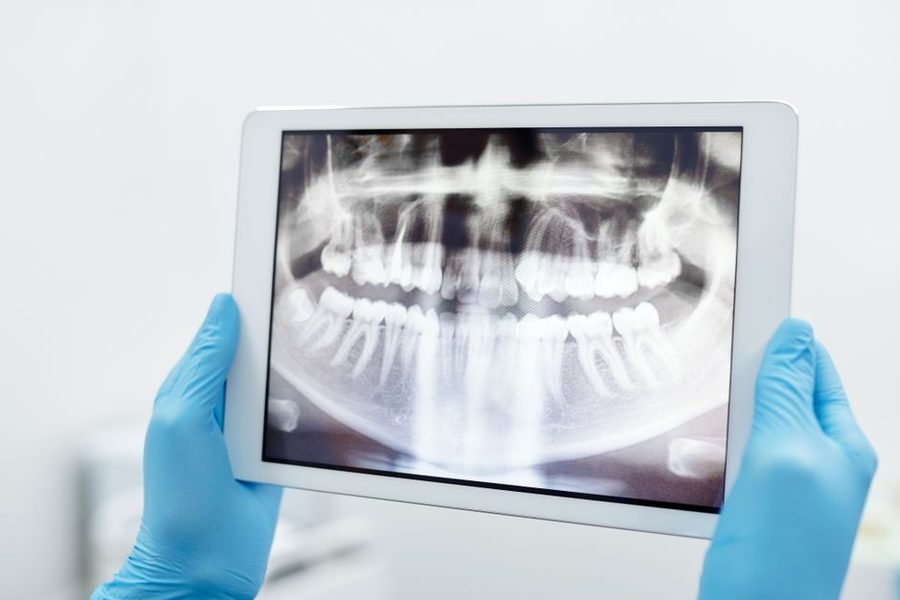
Examination follows. The dentist checks for swelling inside and outside the mouth, taps and presses on teeth, tests hot and cold response, looks for deep decay or fractured cusps, and evaluates mobility and gum health. X-rays are central, though they do not always tell the full story. Early pulp inflammation often causes severe symptoms before major radiographic changes appear. On the other hand, a dark area around a root tip may confirm that infection has already escaped beyond the tooth.
In a well-run emergency visit, the patient should leave with more than a vague answer. They should know whether the goal is immediate root canal therapy, temporary stabilization, referral to an endodontist, extraction, or watchful reassessment within a short window.
Why root canal pain can escalate so quickly
The anatomy of a tooth explains a lot. The pulp chamber and root canals are enclosed spaces. Once inflammation builds there, pressure rises and the tissue has nowhere to expand. Blood flow becomes compromised. Nerves react intensely. That is why pulp pain can feel out of proportion to what is visible from the outside.
Bacteria enter through deep decay, leaking restorations, cracks, or trauma. The body responds, but it is trying to fight infection in a confined structure with limited ability to clear itself. Once bacteria and inflamed tissue extend through the root tip into the surrounding bone and ligament, the problem can move from nerve pain to pressure pain and swelling. At that stage, chewing becomes difficult and even gentle contact can be miserable.
People often ask whether antibiotics alone can “clear it up.” Sometimes antibiotics help control a spreading infection, especially when there is diffuse swelling or systemic involvement. But they do not remove dead or infected pulp tissue from inside the tooth. If the source remains, symptoms often return. This is one of the most common misunderstandings in emergency dental care. Medication can support treatment. It usually does not replace source control.
Same-day root canal versus staged emergency care
A common expectation is that every emergency visit should end with a completed root canal. Sometimes that happens, and it is ideal when the diagnosis is clear, the anatomy is straightforward, and the office has the time and equipment. In other situations, the better emergency treatment is to open the tooth, relieve pressure, remove the inflamed or infected pulp tissue that can be reached safely, place medication if indicated, and seal the tooth temporarily before definitive treatment.
That staged approach is not inferior care. In fact, it can be the most sensible plan when swelling is significant, the patient has limited ability to stay open, the canals are calcified, the tooth has complex anatomy, or the case is likely to need an endodontist’s microscope and advanced imaging. The emergency dentist’s judgment matters here. Good care is not measured by how much gets done in one appointment. It is measured by whether the patient leaves safer, more comfortable, and on a path that gives the tooth the best chance.
There are times when extraction belongs in the conversation right away. If decay extends far below the gumline, if a crack splits the root, if the tooth is too unstable to restore, or if the patient cannot support the cost of root canal and crown therapy, removing the tooth may be more realistic. That can be a hard discussion, especially when someone arrives hoping simply to “save it no matter what.” Honest emergency care includes explaining when preserving a tooth is possible and when it becomes an expensive Emergency Dentist temporary victory.
What treatment usually feels like during an emergency visit
People in pain often fear two things at once, the diagnosis and the procedure. In practice, the emergency part of root canal care is usually easier than the pain that brought the person in. Profound numbness is the first goal. Lower molars can be stubborn, especially when the pulp is acutely inflamed, so achieving anesthesia may take more than one technique. A clinician with emergency experience knows this and does not treat the patient’s continued sensation as anxiety or exaggeration.
Once numbness is achieved, opening the tooth and relieving internal pressure often produces almost immediate change. Patients who arrive tense and sweating sometimes relax within minutes. If pus drains through the canal space or swelling decompresses, the relief can be dramatic. It is not theatrical. It is physiology. Pressure drops, inflammatory load changes, and the tooth stops feeling like it is being squeezed from the inside out.
The rest of the visit depends on the condition of the tooth. Some cases allow full cleaning and shaping of the canals. Others require a temporary dressing and a return visit. If the tooth has lost a lot of structure, the temporary restoration matters more than many patients realize. A weak tooth can fracture between visits if it is not protected, especially a molar that has already been hollowed by decay and access preparation.
Signs you should seek urgent help today
Some situations can wait for the next available dental appointment. Others should not. Delaying treatment can move a manageable tooth problem into a broader infection issue, and in rare cases that becomes medically serious.
- Facial swelling that is enlarging or making it hard to open the mouth
- Fever, chills, or feeling generally unwell along with tooth pain
- Trouble swallowing, drooling, or difficulty breathing
- A severe, deep toothache that prevents sleep and does not respond to basic pain relief
- Trauma to a tooth followed by darkening, severe sensitivity, or swelling
An Emergency Dentist is trained to sort these cases quickly. If breathing or swallowing is affected, hospital-level care may be the safest next step. Dental infections live in the mouth, but they do not always stay there.
The role of antibiotics, pain medication, and home measures
Emergency dental pain makes people creative. They hold aspirin against the gum, rinse with straight liquor, alternate six different products, or hope a leftover antibiotic will buy time. Most of these ideas either do nothing useful or create new problems. Aspirin placed directly on gum tissue can cause a chemical burn. Incomplete antibiotic courses promote confusion and delay proper treatment. Strong mouthwashes can irritate tissues that are already inflamed.
Pain control has a place, but it works best when used rationally. Over-the-counter anti-inflammatory medication often helps with dental pain because much of the discomfort comes from tissue inflammation and pressure. For some adults, combinations of common nonprescription pain relievers can be effective, though the right choice depends on medical history, stomach health, kidney function, bleeding risk, pregnancy status, and other medications. That is why generic online advice has limits. A person on blood thinners, for example, is not in the same category as a healthy college student with a sudden molar ache.
Antibiotics are appropriate when there is swelling, spreading infection, or systemic involvement. They are less useful for pure pulpitis without swelling. This distinction frustrates some patients, especially if they expected a prescription to solve the problem. A responsible emergency dentist explains that pain from an inflamed nerve is not the same as a soft tissue infection and often responds better to definitive dental treatment than to medication alone.
Warm saltwater rinses can soothe irritated tissue around the tooth. Cold compresses on the outside of the face may help if there is swelling. Chewing on the opposite side makes sense. None of these measures replace treatment, but they can help patients get through the hours before they are seen.
Cost, timing, and the real decisions people face
Emergency root canal care sits at the intersection of pain, finances, and uncertainty. That is one reason it feels overwhelming. People are often deciding while exhausted, frightened, and trying to understand unfamiliar terms. If the tooth can be saved, the full pathway commonly includes the emergency exam, X-rays, root canal treatment, and then a core buildup or crown, particularly for back teeth. Molars usually need that extra protection because a root canal-treated tooth can become more brittle over time and has already lost structure from decay or old fillings.
This creates a practical issue. A patient may be able to afford pain relief today but not definitive restoration next month. In the operatory, that matters. Starting a root canal on a tooth that cannot be restored properly later can put the patient in a bad position. On the other hand, extracting a savable tooth because the decision is being made under financial pressure can cause long-term chewing and replacement problems. The best emergency dentists address these trade-offs directly, without pressure or false reassurance.
Timing matters too. Once a tooth is opened and treated, follow-up should not drift for months. Temporary materials are not built for indefinite use, and delays raise the risk of reinfection or fracture. Patients do best when they leave the emergency visit with a concrete next appointment, not just advice to “call if it still hurts.”
What recovery usually looks like
A common surprise after emergency root canal care is that the tooth may still feel sore for a few days, especially when biting. That does not necessarily mean the treatment failed. The ligament around the root can remain inflamed, and tissues that were compressed or infected need time to settle. Most people notice a meaningful drop in the deep, spontaneous pain first. Tenderness to pressure often lingers a bit longer.
If a patient had significant swelling beforehand, recovery can take longer. Drainage may continue briefly. Prescribed antibiotics, when indicated, should be taken exactly as directed. A temporary crown or filling should be treated respectfully. Crunching ice or chewing hard nuts on that side in the first days is an easy way to create a second emergency.
Persistent severe pain, new swelling, fever, or a bite that feels markedly off should prompt contact with the office. Sometimes the issue is as simple as a temporary filling that is slightly high and making the tooth absorb too much force. A minor adjustment can change everything. Other times, there may be additional canals, a fracture, or a spreading infection that needs reevaluation.
Questions worth asking before you leave the chair
When patients are in pain, they tend to remember only half of what they hear. That is normal. It helps to ask focused questions before leaving. You do not need a lecture in dental anatomy. You need practical clarity.
- Is this tooth definitely being treated with a root canal, or is that still provisional?
- Was today’s treatment completed, or is there infected tissue still to be addressed?
- Do I need a crown, and how soon should that happen?
- What symptoms are normal tonight, and what symptoms mean I should call right away?
- If this tooth cannot be saved, what are the replacement options later?
Those answers shape outcomes. They also reduce the confusion that often leads people back into urgent care with the same tooth a week later.
How emergency dentists and endodontists work together
There is sometimes a false divide between general emergency dental care and specialty root canal care. In reality, strong practices collaborate. Many emergency dentists handle straightforward cases very well, especially single-rooted teeth or teeth with clearly identifiable canals and restorability. Endodontists bring added tools for the difficult end of the spectrum, such as calcified canals, retreatments, unusual anatomy, dental trauma, and diagnostic puzzles that do not behave predictably.
A good referral is not a handoff born of uncertainty. It is an informed decision about complexity. Patients benefit when the emergency dentist stabilizes pain, controls infection, documents findings clearly, and gets the patient to the right next provider fast. In some communities, that means same-day specialty referral. In others, it means palliative treatment tonight and specialty care within days. Both can be excellent care when handled deliberately.
A few situations that deserve special caution
Not all patients carry the same risk profile. Someone with diabetes that is poorly controlled may heal more slowly and face a higher infection burden. A patient with a compromised immune system, a history of head and neck radiation, or certain heart conditions may need a more tailored plan. Pregnant patients can absolutely receive emergency dental care, and should when needed, but medication choices and imaging protocols deserve thoughtful handling. Children and teens present another distinct category because trauma, developing teeth, and pain reporting differ from adults.
Then there is the cracked tooth that imitates a root canal emergency but refuses to follow the script. These cases can be the hardest. A tooth may test as though the pulp is involved, yet the deeper issue is a split that changes prognosis dramatically. That is why emergency treatment should always include a discussion of uncertainty when uncertainty truly exists. Experienced clinicians know that honest probability builds more trust than premature certainty.
The value of acting early
Emergency root canal needs rarely begin as emergencies. Most start as small leaks, untreated decay, an old filling that lost its seal, or sensitivity that was inconvenient but tolerable. People delay for understandable reasons, work schedules, money, fear, family obligations. Then one weekend, the threshold is crossed and the tooth demands attention.
The practical lesson is simple. If a tooth starts lingering with heat, waking you at night, or becoming tender to bite, that is the moment to call, not the moment to wait for swelling. Early pulp treatment can sometimes be less invasive, less expensive, and more predictable than care delivered after infection pushes into surrounding tissues. Once the face is involved, the stakes rise.
Emergency dentistry is at its best when it combines speed with judgment. Root canal pain can be intense, but not every painful tooth needs the same answer. The right Emergency Dentist recognizes which cases need immediate intervention, which need stabilization and specialty referral, and which teeth are no longer good candidates for preservation. For patients, that kind of clear-headed care matters as much as the procedure itself. When pain is sharp, sleep is gone, and the side of the face feels wrong, experience shows. So does calm.
Smyle Dental Bakersfield
2016 E St, Bakersfield, CA 93301, United States
+16614939040
FAQ About Emergency Dentist
What counts as a dental emergency?
Severe tooth pain, facial swelling, uncontrolled bleeding, a knocked-out or displaced tooth, and significant dental trauma may need prompt assessment. Trouble breathing or rapidly increasing swelling requires urgent medical help.
What should I do if a permanent tooth is knocked out?
Handle the tooth by the crown rather than the root, keep it moist, and contact a dentist immediately. Fast treatment can improve the chance of saving the tooth.
Can an emergency dentist treat severe tooth pain the same day?
Same-day care may be available depending on the cause and schedule. The dentist will examine the area, may take digital X-rays, and recommend treatment based on the diagnosis.
Should I go to the emergency room for dental swelling?
Seek urgent medical care for trouble breathing, difficulty swallowing, rapidly spreading facial swelling, or other severe symptoms. A dentist can assess the underlying dental cause and provide appropriate follow-up care.